


Marfan Lipodystrophy Syndrome
Patient Information
Characteristics
Background and History
This condition resembles Marfan syndrome in many ways but in addition features an unusual facial appearance and a deficiency of fat (adipose) tissue under the skin. It results from changes (mutations) in the same gene.
Clinical Correlations
Patients are unusually tall with long thin fingers and toes. There may be some growth retardation in the uterus although post-birth growth is usually normal although patients gain weight more slowly than their peers. There is little fatty tissue under the skin (lipodystrophy). Joints are lax and hyperextensible. The face has a somewhat aged appearance (progeroid facies) with a prominent forehead and a small lower jaw. The hard palate is high and narrow and there may be a depression of the sternum. The eyes are larger than normal leading to extreme nearsightedness and the eye lenses are frequently dislocated. The eye openings often slant downward.
Genetics
Inheritance
This is an autosomal dominant disorder in which there is a change (mutation) in a specific gene (the same one as in Marfan syndrome). This mutation is transmitted directly from an affected parent to each child with a 50% probability and therefore such parents can expect that half their children will have the same disorder.
Pedigree
Autosomal dominant
Autosomal dominant disorders require only one mutation for the disease to be expressed. Since an affected parent has two chromosomes, only one of which has the mutant gene, parents can expect that half (50%) of their children will receive that one and inherit the disease. It is common for individuals that inherit the mutation, however, to not have evidence of the disease (nonpenetrance).
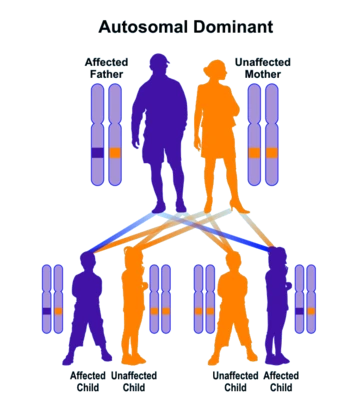
Autosomal dominant inheritance leads to a vertical pattern of transmission
Diagnosis and Prognosis
It is possible that the diagnosis can be made at birth by pediatricians based on the facial and general body appearance. An eye doctor (ophthalmologist) can examine and diagnose the ocular features. A cardiologist should evaluate the heart and aorta to look for structural alterations. Orthopedists should evaluate the skeletal changes such as the joint laxity and sternal and palatal configurations.
There is no treatment available for the general condition but individual features may be surgically repaired. Dislocated lenses in the eye may need to be removed and the retinas periodically evaluated and repaired if they develop holes and detachments (a significant risk due to the extreme near sightedness). Nothing is known about longevity in this disorder.
Printer Friendly Version: Ctrl/Cmd+P