


Clinical Characteristics
Ocular Features
Blue sclerae, especially at infancy, is the most visible ocular sign in osteogenesis imperfecta but it is not always present. It is also often present in normal infants. In some patients, it is present early but disappears later in life. Some patients have significantly lower ocular rigidity, corneal diameters, and decreased globe length. Interestingly, the intensity of the blue color in the sclerae does not seem to be correlated with scleral rigidity.
Systemic Features
A defect in type I collagen leading to brittle bones and frequent fractures is the systemic hallmark of this group of disorders. Clinical and genetic heterogeneity is evident. The nosology is as yet not fully established and will likely require more molecular information. Type I is considered the mildest of the several forms that have been reported. Relatively minor trauma during childhood and adolescence can lead to fractures while adults have less risk. Fractures generally heal rapidly without deformities and with good callous formation in patients with milder disease. However, those with more serious disease often end up with deformities and bowed bones.
Short stature, hearing loss, easy bruising, and dentinogenesis imperfecta are often seen as well.
Type II is more severe and fractures often occur in utero. Fractures may involve long bones, skull bones and vertebrae. At birth the rib case appears abnormally small and the underdeveloped pulmonary system may lead to severe respiratory problems and even death in some newborns.
Genetics
Inheritance
A number of conditions are associated with fragile bones and the classification of these in the early literature is confusing. More confusion arises from classification schemes based solely on clinical degrees of severity.
The designation ‘osteogenesis imperfecta’ is most accurately applied to disorders caused by construction defects in type I collagen fibers which are responsible in 90% of affected individuals. The defect may occur in either the pro-alpha 1 or pro-alpha 2 chains which together form type I collagen. The responsible genes are COL1A1 (17q21.31) and COL1A2 (7q22.1). Clinical types I (166200), IIA (166210), III (259420), and IV (166220) map to these two loci. The inheritance pattern is autosomal dominant.
Mutations in the CRTAP gene (610854; 3p22) cause an autosomal recessive OI-like phenotype classified as type VII while type VIII is an autosomal recessive OI-like disorder secondary to mutations in LEPRE1 (610915; 1p34). However, these disorders, while clinically sharing some features of true OI, are better designated as separate conditions based on their unique molecular etiologies.
Pedigree
Autosomal dominant
Autosomal dominant disorders require only one mutation for the disease to be expressed. Since an affected parent has two chromosomes, only one of which has the mutant gene, parents can expect that half (50%) of their children will receive that one and inherit the disease. It is common for individuals that inherit the mutation, however, to not have evidence of the disease (nonpenetrance).
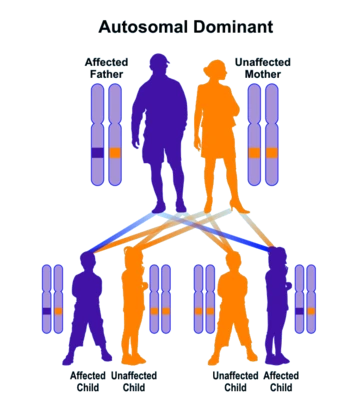
Autosomal dominant inheritance leads to a vertical pattern of transmission