


OMIM ID:
Nystagmus 1, Congenital, X-linked
Alternate Names
Defective Genes
Clinical Characteristics
Ocular Features
Congenital nystagmus is a feature of numerous ocular and systemic disorders. Isolated idiopathic congenital nystagmus (CN), however, refers to a diverse group of abnormal eye movements which are identified usually in the first 6 months of life when no other ocular abnormalities are present. Horizontal eye movements are typical, but vertical and rotary eye movements have also been reported. If the nystagmus is horizontal, the eye movement is usually “to-and-fro”. In general, as the patient gets older, the amplitude of the nystagmus decreases and the frequency of the nystagmus increases, particularly when the patient tries to fixate or look directly at an object. This nystagmus can increase in size and frequency when the patient is tired, sick, or fatigued. Some very young patients are noted to have head nodding or head shaking, but these usually disappear over time. Vision is reduced and varies through the day. Balance may also be affected. Many patients have a “null point” where the eye movement is reduced and vision is improved. They may alter their head position in an effort to maximize their acuity.
Strabismus and amblyopia often develop.
Systemic Features
No consistent systemic abnormalities have been reported.
Genetics
Inheritance
Different heritable patterns of idiopathic congenital nystagmus, including autosomal dominant and recessive, and X-linked recessive, have been found. A variety of mutations in the FRMD7 (Xq26.2) gene (containing 12 exons) have been identified in many families with an X-linked recessive pattern.
Another mutation associated with X-linked congenital nystagmus is GPR143 at Xp22.3 causing NYS6 (300814). A locus at Xp11.4-p11.3 contains an as yet unknown mutation responsible for an infantile periodic alternating type: NYS5 (300589).
Several autosomal dominant forms have been linked to chromosomal regions 6p12 (NYS2; 164100), 7p11 (NYS3, 608345), 13q (NYS4, 193003), 1q31.3-q32.1, and NYS7 (614826). Autosomal recessive inheritance has been proposed for several pedigrees but adequate documentation is lacking (see 257400).
Pedigree
Autosomal dominant
Autosomal dominant disorders require only one mutation for the disease to be expressed. Since an affected parent has two chromosomes, only one of which has the mutant gene, parents can expect that half (50%) of their children will receive that one and inherit the disease. It is common for individuals that inherit the mutation, however, to not have evidence of the disease (nonpenetrance).
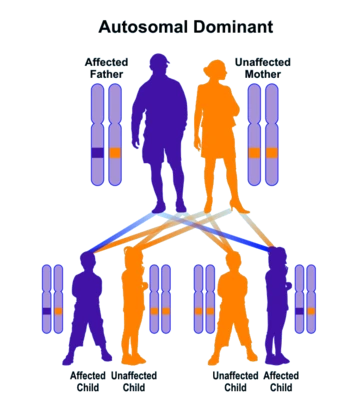
Autosomal dominant inheritance leads to a vertical pattern of transmission
Autosomal recessive
In order for autosomal recessive disorders to be expressed, offspring generally must inherit two mutations, one from each carrier parent. Carriers with only one mutation, such as the parents, do not have clinical disease. Note that carrier parents can expect that 1 in 4 children (25%) will inherit both mutations and have the disorder, 2 in 4 children (50%) will be carriers like their parents, while 1 in 4 children (25%) inherit neither mutation.

In order for autosomal recessive disorders to be expressed, offspring generally must inherit two mutations, one from each carrier parent. Carriers with only one mutation, such as the parents, do not have clinical disease. Note that carrier parents can expect that 1 in 4 children (25%) will inherit both mutations and have the disorder, 2 in 4 children (50%) will be carriers like their parents, while 1 in 4 children (25%) inherit neither mutation.
X-linked recessive, carrier mother
X-linked disorders are caused by a mutation on the X chromosome and both sexes can pass this to their children. If the mutation is in a recessive gene and carried by the mother, she usually does not have the disease since the normal X chromosome without the mutation neutralizes the mutation in the abnormal X chromosome. However, half her sons will inherit the mutation-containing X chromosome and therefore have the X-linked disease. Half the daughters will inherit the mutation-bearing X chromosome and are usuallly healthy 'carriers'.

X-linked disorders are caused by a mutation on the X chromosome and both sexes can pass this to their children. If the mutation is in a recessive gene and carried by the mother, she usually does not have the disease since the normal X chromosome without the mutation neutralizes the mutation in the abnormal X chromosome. However, half her sons will inherit the mutation-containing X chromosome and therefore have the X-linked disease. Half the daughters will inherit the mutation-bearing X chromosome and are usuallly healthy 'carriers'.
X-linked recessive, father affected
X-linked disorders are caused by a mutation on the X chromosome and both sexes can pass this to their children. If the mutation is in a recessive gene and carried by the father, he has the disease since his only X chromosome is mutant and he has no normal X to blunt the effects of the abnormal gene. His sons only receive his Y chromosome and thus are all normal. However, all his daughters receive his one and only X chromosome and will be healthy 'carriers'. Thus such males will have no affected children but half their grandsons from those daughters will have the same disease as he does.

X-linked disorders are caused by a mutation on the X chromosome and both sexes can pass this to their children. If the mutation is in a recessive gene and carried by the father, he has the disease since his only X chromosome is mutant and he has no normal X to blunt the effects of the abnormal gene. His sons only receive his Y chromosome and thus are all normal. However, all his daughters receive his one and only X chromosome and will be healthy 'carriers'. Thus such males will have no affected children but half their grandsons from those daughters will have the same disease as he does.