


OMIM ID:
Corneal Dystrophy, Fuchs Endothelial, Late Onset
Alternate Names
Defective Genes
Clinical Characteristics
Ocular Features
There are a number of endothelial corneal dystrophies to which Fuchs name has been attached, including two that are early in onset, or even congenital (CHED1; 121700), (CHED2; 217700) and at least three that have an adult onset, one (Fuchs endothelial dystrophy, early onset; 136800) which has a relatively early onset and two considered to have a late onset: the one described here and another known as Fuchs Endothelial Dystropy, Late Onset 2 (613267). Evidence for multiple distinct types comes from genotyping which reveals considerable genetic heterogeneity in spite of similar phenotypes (see Genetics). All are progressive and degenerative with various degrees of visual disability. Most have histologic changes in both the endothelial cells and Descemet membrane.
The entity described here likely is the classical disease described in the older literature. It is certainly the most common, occurring in 4% of the population over the age of 40 years and for unknown reasons is more often found in females. Guttae are formed as excrescences of Descemet’s membrane and develop initially in the central cornea, beginning about the 5th decade, gradually increasing in number and size toward the periphery. They tend to be relatively large, sharply peaked and often positioned at the cell-cell junctions of endothelial cells. These are often best visualized by corneal transillumination. Histologically, the posterior portion of Descemet membrane contains bundles and sheets of abnormal collagen. Progressive corneal edema follows as endothelial cells are lost and the remaining ones are unable to maintain normal stromal hydration. Fingerprint lines may be present. The corneal edema may involve both stroma and epithelium and in advanced stages may lead to painful epithelial erosions. The disease is relentless and early blurring of vision progresses to significant visual handicaps often requiring corneal transplantation in the 7th and 8th decades.
Corneal guttae are common in older individuals but usually are located more peripherally. The diagnosis of Fuchs can best be made where the guttae are concentrated centrally and associated with stromal and epithelial edema.
Systemic Features
No systemic abnormalities have been reported.
Genetics
Inheritance
Late onset Fuchs of this type is due to a mutation on chromosome 13 (13pter-q12.13) but the specific molecular basis for the disease remains unclear. Many cases occur sporadically but some pedigrees are consistent with autosomal dominant inheritance. For unknown reasons females are more commonly affected and often have more severe disease. Recent reports suggest that missense mutations in ZEB1 may be responsible for at least some cases of late-onset Fuchs. This mutation has also been found in cases of type 3 posterior polymorphous dystrophy (609141) suggesting that the two conditions may be allelic.
Other rare forms of late onset endothelial dystrophy to which the eponymic designation of Fuchs has been applied include FECD3 (613267) in which various mutations in the TCF4 locus on chromosome 18 (18q21.2-q21.3) (and expanded TGC trinucleotide repeats) have been implicated. Other variants of Fuchs endothelial dystrophy include FECD4 (613268) with a mutation in SLC4A11 (20p13-p12), FECD5 (613269) with a possible mutation on chromosome 5 (5q33.1-q35.2), FECD6 (613270) due to a mutation in ZEB1 on chromosome 10 (10p11.2), and FECD7 (613271) that can be mapped to chromosome 9 (9p24.1-p22.1).
Pedigree
Autosomal dominant
Autosomal dominant disorders require only one mutation for the disease to be expressed. Since an affected parent has two chromosomes, only one of which has the mutant gene, parents can expect that half (50%) of their children will receive that one and inherit the disease. It is common for individuals that inherit the mutation, however, to not have evidence of the disease (nonpenetrance).
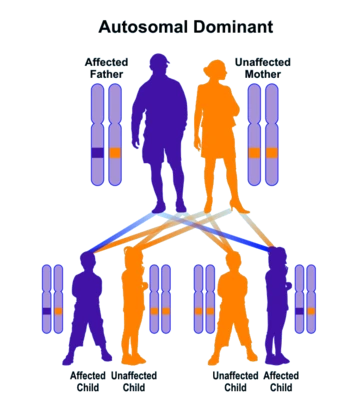
Autosomal dominant inheritance leads to a vertical pattern of transmission