


Intellectual Disability with Dysmorphic Facies and Ptosis
Patient Information
Characteristics
Background and History
A large number of gene mutations can impact brain function resulting in various degrees of intellectual dysfunction. Many such disorders, including this one, cause skeletal abnormalities and physiologic dysfunction as well.
Clinical Correlations
In this condition the facial features are not diagnostic but together suggest the diagnosis. The face is round and flat with the eyes set wide apart. The skull is often somewhat small and the lids usually droop (ptosis). Low birth weight is common and general growth is slow resulting in short stature. Infants feed poorly as well. They have poor muscle tone and are floppy with loose joints. Movements of the limbs are often uncoordinated. Developmental milestones are achieved late if at all. In particular, expressive speech is slow to develop but general intellectual disability is mild. The digits are often shortened and there may be abnormalities in the upper vertebrae.
MRI studies may reveal some brain anomalies. Seizures develop in some patients.
Genetics
Inheritance
Mutations in a specific gene are responsible for this condition which appears in an autosomal dominant pattern. Thus, this disorder theoretically could be transmitted directly from parent to child but the physical and mental difficulties in most individuals prevent reproduction.
Pedigree
Autosomal dominant
Autosomal dominant disorders require only one mutation for the disease to be expressed. Since an affected parent has two chromosomes, only one of which has the mutant gene, parents can expect that half (50%) of their children will receive that one and inherit the disease. It is common for individuals that inherit the mutation, however, to not have evidence of the disease (nonpenetrance).
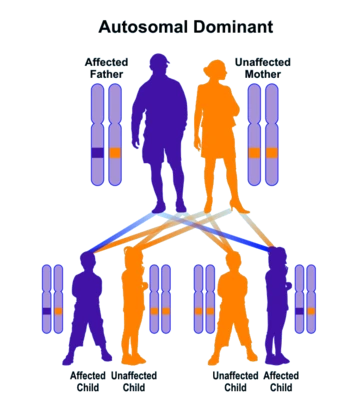
Autosomal dominant inheritance leads to a vertical pattern of transmission
Diagnosis and Prognosis
General failure to thrive and feeding difficulties become apparent in infancy. Pediatricians, neurologists and others are likely to collaborate in making the diagnosis. MRI studies of the brain may be helpful but are not diagnostic. The lack of normal muscular function, slow growth, facial dysmorphism (especially droopy eyelids), and the onset of seizures coupled with delayed achievement of normal developmental milestones (sitting, walking, and talking) evident later in childhood are important signs that point to this disorder.
No information regarding longevity is available but some patients live to adulthood.
Printer Friendly Version: Ctrl/Cmd+P