


Gabriele-de Vries Syndrome
Patient Information
Characteristics
Background and History
This recently reported hereditary syndrome has numerous congenital features evident from birth. Intrauterine growth is subnormal and general development from birth is slow.
Clinical Correlations
Growth in the womb is below normal. Feeding difficulties begin at birth and likely contribute to the overall delay in physical and mental growth. Milestones such as walking and speech are delayed. There is a variable amount of cognitive impairment with features of autism and anxiety. There are often tremors and stiff movements.
The facial morphology is highly variable but nonspecific. The forehead is usually prominent, the ears are rotated posteriorly, the midface (cheek area) is flat and underdeveloped. The lower jaw is abnormally small. The eyelids usually seem abnormally full, mostly in the upper lid, and there may be some drooping of the upper lids as well. The eyebrows are sparse.
Brain imaging shows a variety of abnormal features suggesting abnormal maturation.
Genetics
Inheritance
This is an autosomal dominant condition in which one would expect a vertical pattern of inheritance. However, the severity of the clinical features precludes reproduction in virtually all cases and therefore most cases occur de novo (without a family history).
Pedigree
Autosomal dominant
Autosomal dominant disorders require only one mutation for the disease to be expressed. Since an affected parent has two chromosomes, only one of which has the mutant gene, parents can expect that half (50%) of their children will receive that one and inherit the disease. It is common for individuals that inherit the mutation, however, to not have evidence of the disease (nonpenetrance).
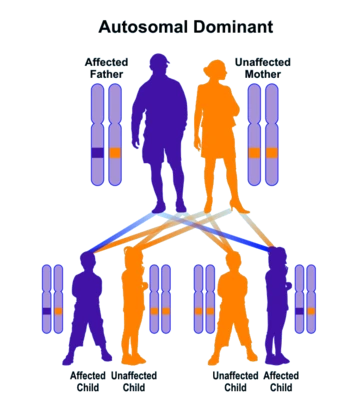
Autosomal dominant inheritance leads to a vertical pattern of transmission
Diagnosis and Prognosis
The pattern of congenital malformations could allow a tentative diagnosis at birth but most of these are nonspecific and genotyping is necessary for the final diagnosis. Pediatricians and neurologists will likely collaborate on the evaluation and care of these children.
Early developmental intervention and training would likely be beneficial. There is no reported general treatment that is helpful but special education should be considered in appropriate individuals. No information on longevity is available and lifelong supportive care is required.
Printer Friendly Version: Ctrl/Cmd+P