


External Ophthalmoplegia, Facial Weakness, and Malignant Hyperthermia
Patient Information
Characteristics
Background and History
Mutations in certain genes increase the risk of an uncontrolled elevation in body temperature during general anesthesia following the administration of certain drugs. Along with increases in body temperature, there may be muscle rigidity, breakdown of muscle fibers, a rapid heart rate, and metabolic abnormalities. The condition must be recognized and treated promptly to prevent a fatal outcome.
The underlying condition, known as malignant hyperthermia (fever) susceptibility (MHS1), usually results from an inherited disruption in muscle calcium regulation. A number of other abnormalities in muscle, both of the eye and of the skeleton, have been identified among susceptible individuals, including this condition in which the eyes do not move normally, the facial muscles are weak, and the eyelids droop. Similar muscle problems also occur in the absence of malignant hyperthermia.
Clinical Correlations
A subset of patients with MHS1 has facial muscle weakness, droopy eyelids (ptosis), and difficulty moving the eyes. This may or may not be associated with generalized muscle weakness which may be progressive. In patients with severe disease, this may lead to breathing difficulties and abnormal curvature of the spine. The susceptibility to malignant hyperthermia is not evident until persons undergo general anesthesia.
Most individuals with one of the mutations that raise the risk of developing a high fever during or after general anesthesia live normal lives and the potential of developing malignant hyperthermia remains unknown. Certain commonly used anesthetic gases such as halothane combined with another drug, succinylcholine, seem to be primarily responsible and should be avoided in susceptible individuals. Prompt detection and treatment are essential to avoid the complications of muscle breakdown, metabolic abnormalities, kidney failure and death.
Genetics
Inheritance
This category of disease, known as MHS1, likely consists of several conditions. It is usually inherited in an autosomal dominant pattern in which parents pass the gene mutation to each child with a 50% probability. However, the subset of individuals with the muscle problems described here seem to require the presence of two mutations and the condition follows an autosomal recessive pattern in which normal parents (that carry only one copy of the mutation) confer a risk of 25% for MHS1 to each child.
Other gene mutations may also confer susceptibility to malignant hyperthermia.
Pedigree
Autosomal dominant
Autosomal dominant disorders require only one mutation for the disease to be expressed. Since an affected parent has two chromosomes, only one of which has the mutant gene, parents can expect that half (50%) of their children will receive that one and inherit the disease. It is common for individuals that inherit the mutation, however, to not have evidence of the disease (nonpenetrance).
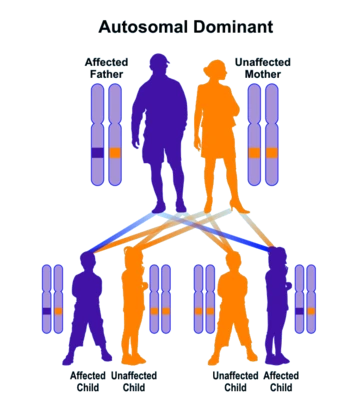
Autosomal dominant inheritance leads to a vertical pattern of transmission
Autosomal recessive
In order for autosomal recessive disorders to be expressed, offspring generally must inherit two mutations, one from each carrier parent. Carriers with only one mutation, such as the parents, do not have clinical disease. Note that carrier parents can expect that 1 in 4 children (25%) will inherit both mutations and have the disorder, 2 in 4 children (50%) will be carriers like their parents, while 1 in 4 children (25%) inherit neither mutation.

In order for autosomal recessive disorders to be expressed, offspring generally must inherit two mutations, one from each carrier parent. Carriers with only one mutation, such as the parents, do not have clinical disease. Note that carrier parents can expect that 1 in 4 children (25%) will inherit both mutations and have the disorder, 2 in 4 children (50%) will be carriers like their parents, while 1 in 4 children (25%) inherit neither mutation.
Diagnosis and Prognosis
The diagnosis of malignant hyperthermia is usually made by the anesthesiologist during or soon after general anesthesia is administered. The administration of anesthetic gas must be terminated and body cooling begun. Intravenous injection of a drug called dandrolene sodium should be administered promptly and any blood chemical imbalances corrected promptly. Prompt diagnosis and vigorous treatment reduces the risk of serious complications but absent these measures the fatality rate is high. It is important that patients who experience malignant hyperthermia inform other family members so that they can provide this history whenever general anesthesia will be used. Knowledge of pre-existing susceptibility enables the anesthesiologist to use alternate drugs to reduce the risk.
There is some evidence that rare individuals may experience the full syndrome when body heat rises during intense exercise.
Certain individuals might benefit from surgery to lift the eyelids.
Web Resources
Printer Friendly Version: Ctrl/Cmd+P