


OMIM ID:
Smith-Magenis Syndrome
Alternate Names
Defective Genes
Clinical Characteristics
Ocular Features
Ocular abnormalities have been found in the majority of patients. Microcornea, myopia, strabismus and iris dysplasia are the most common. Rare patients have iris colobomas or correctopia. The eyes appear deep-set and lid fissures are upward slanting.
Systemic Features
The facial features are considered to be distinctive, characterized by a broad, square face, prominent forehead, broad nasal bridge, and midface hypoplasia. These and other features appear more pronounced with age as in the size of the jaw which is underdeveloped in infancy and eventually becomes prognathic. Most patients have developmental delays, speech and motor deficits, cognitive impairments and behavioral abnormalities. Hypotonia, hyporeflexia, failure to thrive, lethargy, and feeding difficulties are common in infants. Older individuals have REM sleep disturbances with self-destructive behaviors, aggression, inattention, hyperactivity, and impulsivity. Short stature, hypodontia, brachydactyly, hearing loss, laryngeal anomalies, and peripheral neuropathy are common. Seizures are uncommon.
The behavioral profile of this syndrome can resemble that of autism spectrum disorders although symptoms of compulsivity are more mild.
A related developmental disorder known as Potacki-Lupski syndrome (610883) involving the same locus on chromosome 17 has a similar behavioral profile. Ocular and systemic malformations may be less severe though.
Genetics
Inheritance
Most patients (90%) with the Smith-Magenis syndrome have interstitial deletions in the short arm of chromosome 17 (17p11.2). However, it is included here since a few have heterozygous molecular mutations in the RAI1 gene which is located in this region. While there is considerable phenotypic overlap, individuals with chromosomal deletions have the more severe phenotype as might be expected. For example, those with RAI1 mutations tend to be obese and are less likely to exhibit short stature, cardiac anomalies, hypotonia, hearing loss and motor delays than seen in patients with a deletion in chromosome 17. However, the phenotype is highly variable among patients with deletions depending upon the nature and size of the deletion.
The retinoic acid induced 1 gene (RAI1) codes for a transcription factor whose activity is reduced by mutations within it.
Familial cases are rare and reproductive fitness is virtually zero. If parental chromosomes are normal, the risk for recurrence in sibs is less than 1%. Males and females are equally affected.
In Potocki-Lupski syndrome (610883) there is duplication of the 17p11.2 microdeletion as the reciprocal recombination product of the SMS deletion.
Pedigree
Autosomal dominant
Autosomal dominant disorders require only one mutation for the disease to be expressed. Since an affected parent has two chromosomes, only one of which has the mutant gene, parents can expect that half (50%) of their children will receive that one and inherit the disease. It is common for individuals that inherit the mutation, however, to not have evidence of the disease (nonpenetrance).
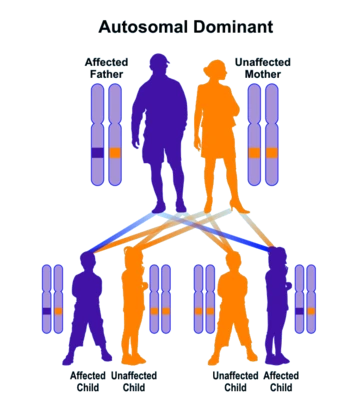
Autosomal dominant inheritance leads to a vertical pattern of transmission