


OMIM ID:
Macular Dystrophy, Vitelliform 3
Alternate Names
Defective Genes
Clinical Characteristics
Ocular Features
Patients generally become symptomatic (reduced vision and metamorphopsia) in the fourth and fifth decades. Vision loss is mild as in vitelliform 1 disease and only slowly progressive in most patients. One or sometimes more small, oval, and slightly elevated yellow lesions resembling an egg yolk may be seen in the fovea along with paracentral drusen and mild RPE changes. The fundus changes can appear any time in adult life but little is known about their nature history. The EOG light/dark ratio may be normal or slightly decreased and the ERG likewise can be normal or, in some cases, reveals rod and cone system abnormalities. Optical coherence tomography shows yellowish deposits between the neurosensory retina and the RPE with foveal thinning. Color vision has been described as normal. The visual field may show peripheral constriction or central scotomas. Choroidal neovascularization occurs rarely.
Variability in the clinical features often leads to misdiagnosis in individual patients who are sometimes considered to have age-related macular degeneration, retinitis pigmentosa, fundus flavimaculatus, dominant drusen, butterfly macular dystrophy, and pattern dystrophy.
Systemic Features
No systemic abnormalities have been reported.
Genetics
Inheritance
This is an autosomal dominant condition resulting from heterozygous mutations in the RDS (PRPH2) gene (6p21.1).
The gene product of PRPH2 is active in the retina. It is important to the integrity and stability of the structures that contain light-sensitive pigments (e.g., photoreceptors). More than 100 mutations have been identified. The resultant phenotype can be highly variable, even within members of the same family but most affected individuals have some degree of pigmentary retinopathy within the macula or throughout the posterior pole. The altered gene product resulting from mutations in PRPH2 often leads to symptoms beginning in midlife as a result of the slow degeneration of photoreceptors. This database contains at least 11 disorders in which PRPH2 mutations have been found.
Genotyping has identified at least 5 forms of vitelliform macular dystrophy. In addition to the iconic Best disease (VMD2, 153700) apparently first described by Friedreich Best in 1905 and now attributed to mutations in the Best1 gene, we know of at least 4 more and specific mutations have been identified in three. No mutation or locus has yet been identified in VMD1 (153840) but it is likely a unique condition since mutations in other genes known to cause vitelliform dystrophy have been ruled out. Other forms are VMD3 described here, VMD4 (616151) resulting from mutations in the IMPG1 gene, and VMD5 (616152) caused by mutations in the IMPG2 gene.
Pedigree
Autosomal dominant
Autosomal dominant disorders require only one mutation for the disease to be expressed. Since an affected parent has two chromosomes, only one of which has the mutant gene, parents can expect that half (50%) of their children will receive that one and inherit the disease. It is common for individuals that inherit the mutation, however, to not have evidence of the disease (nonpenetrance).
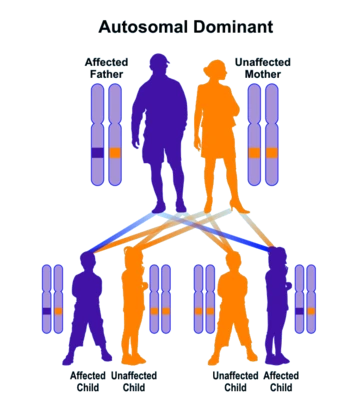
Autosomal dominant inheritance leads to a vertical pattern of transmission