


OMIM ID:
Corneal Dystrophy, Lattice Type II
Alternate Names
Defective Genes
Clinical Characteristics
Ocular Features
This is a systemic amyloidosis disorder with significant corneal disease. The corneal stroma contains linear deposits which are more discrete, more peripheral, more delicate, and more radial than those in lattice type I with which it is sometimes confused. There is also less accumulation of amorphous amyloid material than in type I. The onset is often later as well, and rarely seen in childhood. Corneal sensitivity is reduced. Vision is less affected than in type I lattice dystrophy and patients rarely require keratoplasty, and, if so, later in life.
Amyloid deposits are found in the cornea, sclera, choroid, lacrimal gland, ciliary nerves, and adnexal blood vessels. Ptosis and extraocular muscle dysfunction is not significant.
Systemic Features
Amyloid deposits are found throughout the body including blood vessels, heart, kidney, skin and nerves. A “mask-like” facies with a protruding lower lip, dry itchy skin, peripheral and cranial neuropathy, and renal failure are clinical features but often have their onset late in life. Facial paralysis and bulbar palsy may be the result.
Genetics
Inheritance
While this is considered an autosomal dominant disorder, presumed homozygous cases have been reported in Finland where the first cases were described. These cases seem to have more severe disease with an earlier onset than found among patients with heterozygous mutations. Mutations in the GSN gene located at 9q34 are responsible.
Pedigree
Autosomal dominant
Autosomal dominant disorders require only one mutation for the disease to be expressed. Since an affected parent has two chromosomes, only one of which has the mutant gene, parents can expect that half (50%) of their children will receive that one and inherit the disease. It is common for individuals that inherit the mutation, however, to not have evidence of the disease (nonpenetrance).
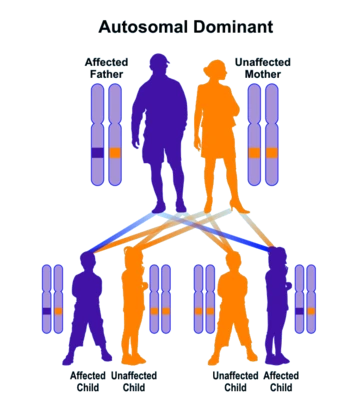
Autosomal dominant inheritance leads to a vertical pattern of transmission