


OMIM ID:
Tuberous Sclerosis 1
Alternate Names
Defective Genes
Clinical Characteristics
Ocular Features
The primary clinical characteristic of tuberous sclerosis of both types 1 and 2 are the occurrence of hamartomas at multiple anatomic sites. Ocular lesions include those of the eyelids which often appear in early childhood along with other facial angiofibromas (formerly called adenoma sebaceum). Of greater clinical significance are lesions of the optic nerve and retina reported in about 75% of patients. The latter (astrocytic hamartomas) may appear as mulberry-like growths typically located in the peripapillary area or as flat translucent lesions located more peripherally. These are usually static but aggressive growth with retinal detachment and neovascular glaucoma requiring enucleation has been reported in several patients. Calcification of these lesions may occur in utero or early in life. These are seldom of clinical significance although optic atrophy has been reported. The iris may have hypopigmented areas.
Systemic Features
Hamartomas develop throughout the body in many organs such as the skin, brain, eye, kidney, and heart. Ninety per cent of patients have skin lesions, including hypomelanotic patches called ‘ashleaf’ spots that can best be visualized under a Woods lamp. Symptoms vary widely depending upon the location and size of the growths. These appear as rhabdomyomas in the heart, angiomyolipomas in the kidneys, bone cysts, and oral fibromas. Other intracranial growths such as subependymal astrocytomas and cortical tubers are evidence of CNS involvement that can interfere with brain function leading to seizures (in 80% of patients) and subnormal intellectual abilities (60-70% patients) as manifested by learning difficulties, subnormal IQs, as well as social and communication difficulties. Hypoplasia of dental enamel with pitting in permanent teeth is seen in the majority of patients. Some progression of tumor size and symptoms may occur. Most hamartomas are benign but renal carcinoma has been reported in some patients.
Genetics
Inheritance
Many cases (two-thirds) occur sporadically but numerous reported pedigrees are consistent with autosomal dominant inheritance. Type 1 TSC is caused by mutations in the TSC1 gene (9p34) encoding hamartin and is responsible for the disorder in about 25% of patients.
A more severe phenotype, tuberous sclerosis 2 (613254), is caused by mutations in the TSC2 gene on chromosome 16p13.3 and accounts for the majority of cases of tuberous sclerosis complex. Genotyping is necessary to determine which mutation is responsible for the TS complex in each case as the phenotypic differences are inadequate to distinguish clinically between types 1 and 2.
New mutations are responsible for 50-70% of cases.
Pedigree
Autosomal dominant
Autosomal dominant disorders require only one mutation for the disease to be expressed. Since an affected parent has two chromosomes, only one of which has the mutant gene, parents can expect that half (50%) of their children will receive that one and inherit the disease. It is common for individuals that inherit the mutation, however, to not have evidence of the disease (nonpenetrance).
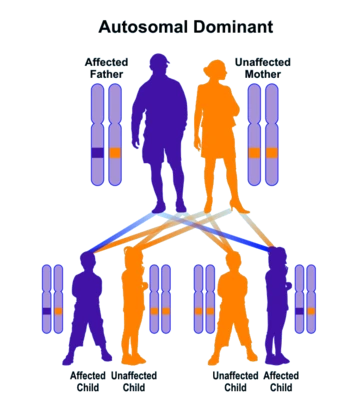
Autosomal dominant inheritance leads to a vertical pattern of transmission