


Watson Syndrome
Patient Information
Characteristics
Background and History
This syndrome was first described by GH Watson, a British physician trained in pediatrics, in 1967. It bears close resemblance to neurofibromatosis described elsewhere in this database. In fact, there is evidence that mutations in the same gene are responsible.
Clinical Correlations
Short stature and low normal intelligence seem to be common among all patients. Most patients also have some obstruction in the pulmonary valve of the artery which carries blood to the lungs. Pigmented skin lesions called café-au-lait spots are frequently present. The head is relatively large compared to other bodily proportions.
A few individuals have small nerve tumors and small growths on the iris, the colored part of the eye that forms the pupil. Vision is not affected.
Genetics
Inheritance
A gene mutation is responsible for the Watson syndrome. It is inherited in an autosomal dominant pattern and affected parents can expect that half of their children will inherit it.
Pedigree
Autosomal dominant
Autosomal dominant disorders require only one mutation for the disease to be expressed. Since an affected parent has two chromosomes, only one of which has the mutant gene, parents can expect that half (50%) of their children will receive that one and inherit the disease. It is common for individuals that inherit the mutation, however, to not have evidence of the disease (nonpenetrance).
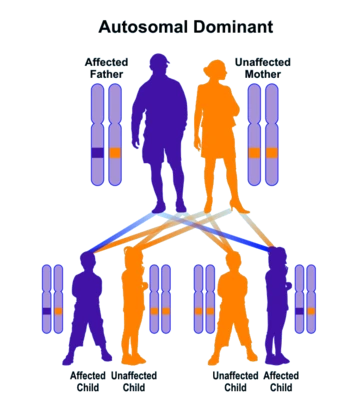
Autosomal dominant inheritance leads to a vertical pattern of transmission
Diagnosis and Prognosis
The diagnosis is most likely made by a pediatrician, perhaps in consultation with a neurologist and an ophthalmologist. No treatment is available for the syndrome but multidisciplinary management for isolated problems may be necessary. No information regarding longevity is available and most individuals can expect to live normal lives without significant handicaps.
Web Resources
Printer Friendly Version: Ctrl/Cmd+P