


Waardenburg Syndrome, Type 2
Patient Information
Characteristics
Background and History
Waardenburg syndrome is named after a Dutch ophthalmologist, Petrus Johannes Waardenburg who first described it in 1951. It has since been subdivided into several types all of which have some features in common.
Clinical Correlations
Features in common in types 1 through 4 include: patches of skin and hair that have less pigment, irises that may be colored differently, and a congenital hearing loss. Hearing may be normal in some patients while sometimes deafness occurs in only one ear. Hearing loss is the most significant clinical problem and is usually congenital and sometimes profound. Some types and maybe all have pigmentary changes in the retina. Areas of the iris that do not pigment normally are described as having a brilliant blue color. The root of the nose is often prominent and broad, and the eyebrows can be bushy with hair growing between them (synophrys).
Most patients with the Waardenburg syndrome have no systemic disease other than the hearing loss. Certain types, however, may have some limb and digit malformations with fused fingers and mild underdevelopment of arms and legs. Another type (4) is associated with an abnormality in the colon called Hirschsprung disease which results in dilation of the colon and improper emptying. These types are rare, however.
Genetics
Inheritance
Most types of Waardenburg syndrome are inherited in an autosomal dominant pattern in which the disorder is passed directly from parent to child in a vertical pattern. An affected parent in this case can expect that the syndrome will appear in half of his/her children. However, kindreds have been reported in which the pattern is more consistent with autosomal recessive inheritance in which case the disorder appears in sibs born to normal parents. In this case, the parents are often related.
Pedigree
Autosomal dominant
Autosomal dominant disorders require only one mutation for the disease to be expressed. Since an affected parent has two chromosomes, only one of which has the mutant gene, parents can expect that half (50%) of their children will receive that one and inherit the disease. It is common for individuals that inherit the mutation, however, to not have evidence of the disease (nonpenetrance).
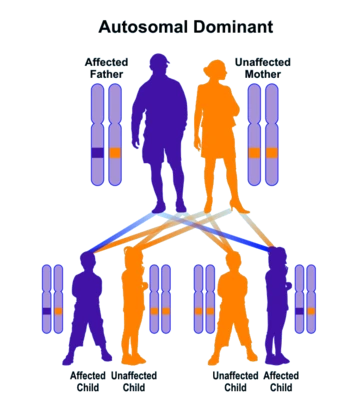
Autosomal dominant inheritance leads to a vertical pattern of transmission
Autosomal recessive
In order for autosomal recessive disorders to be expressed, offspring generally must inherit two mutations, one from each carrier parent. Carriers with only one mutation, such as the parents, do not have clinical disease. Note that carrier parents can expect that 1 in 4 children (25%) will inherit both mutations and have the disorder, 2 in 4 children (50%) will be carriers like their parents, while 1 in 4 children (25%) inherit neither mutation.

In order for autosomal recessive disorders to be expressed, offspring generally must inherit two mutations, one from each carrier parent. Carriers with only one mutation, such as the parents, do not have clinical disease. Note that carrier parents can expect that 1 in 4 children (25%) will inherit both mutations and have the disorder, 2 in 4 children (50%) will be carriers like their parents, while 1 in 4 children (25%) inherit neither mutation.
Diagnosis and Prognosis
In most cases no treatment is required. Fused fingers can sometimes be separated, deafness may be treated with hearing aids, and colon malfunction can be surgically treated. Lifespan is normal.
Web Resources
Printer Friendly Version: Ctrl/Cmd+P