


Duane Retraction Syndrome 1
Patient Information
Characteristics
Background and History
Duane syndrome is a congenital, non-progressive disorder of eye movement first described by an American ophthalmologist, Alexander Duane, in 1905. It occurs most often as a sporadic, non-familial condition but is sometimes inherited. It is also a part of several syndromes that include anomalies in other parts of the body.
Clinical Correlations
Inherited Duane syndrome when it occurs in the absence of other malformations is often bilateral. The essential features are difficulty in moving the eye to the side, and a narrowing of the space between the eyelids when the eye moves toward the nose. The eyes in the majority of individuals do not line up straight (strabismus) when looking straight ahead and often the patient assumes a head turn to avoid double vision. This is not always effective and about 10% of patients develop a lazy eye (amblyopia). Evidence suggests that the nerves that innervate the eye muscles do not develop normally resulting in weakness of such muscles and difficulty moving the eye in the desired direction. Vision in each eye, however, is normal unless amblyopia develops.
Genetics
Inheritance
Only the inherited type of Duane syndrome is discussed here and the pattern of transmission is usually autosomal dominant. That is, the disorder is passed directly from parent to child with an expected ratio of affected offspring of 50%.
Pedigree
Autosomal dominant
Autosomal dominant disorders require only one mutation for the disease to be expressed. Since an affected parent has two chromosomes, only one of which has the mutant gene, parents can expect that half (50%) of their children will receive that one and inherit the disease. It is common for individuals that inherit the mutation, however, to not have evidence of the disease (nonpenetrance).
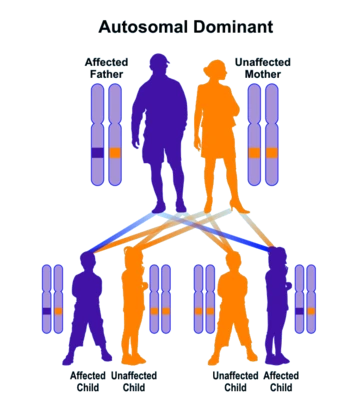
Autosomal dominant inheritance leads to a vertical pattern of transmission
Diagnosis and Prognosis
This disorder is usually diagnosed by an ophthalmologist, often during the neonatal period. Because of the variable nature of presentation, no single treatment can be prescribed. In mild cases, prisms in glasses might be sufficient, but for those with a severe head turn or unusual movements of the eyes various surgical treatments can be effective. All children must be followed carefully during the first decade of life since treatment for amblyopia is usually most effective if diagnosed early. Left untreated, the loss of vision and depth perception can become permanent.
Web Resources
Printer Friendly Version: Ctrl/Cmd+P