


Baker-Gordon Syndrome
Patient Information
Characteristics
Background and History
Approximately a dozen patients have been reported in the last decade with features of this neurodevelopmental disorder. All have been isolated cases without a family history.
Clinical Correlations
Global development delay is a common feature. Hypotonia may be evident from birth. Walking and speech are delayed and moderate to profound intellectual impairment is virtually always present. Involuntary movements such as dystonia, ataxia, dyskinesias, and choreoathetosis are often seen. Abnormal behaviors such as outbursts of anger, poor attention span, head-banging, and self-mutilation are common. Central sleep apnea has been described.
Facial features are described as “fine” and patients often have decreased vision described as central in origin. Eye contact and visual attention are poor. Many individuals have strabismus, hypermetropia, and nystagmus. Other physical features include a high forehead, scoliosis, joint laxity, and foot deformities.
The EEG may show a variety of non-specific abnormalities but seizures have not been described. Brain imaging has revealed delayed myelination and periventricular white matter abnormalities in a few individuals.
Genetics
Inheritance
All individuals so far have been isolated cases without a family history of similar disease. For this reason, the presumably causative gene mutation found in eleven individuals with this condition is considered to occur de novo.
Pedigree
Autosomal dominant
Autosomal dominant disorders require only one mutation for the disease to be expressed. Since an affected parent has two chromosomes, only one of which has the mutant gene, parents can expect that half (50%) of their children will receive that one and inherit the disease. It is common for individuals that inherit the mutation, however, to not have evidence of the disease (nonpenetrance).
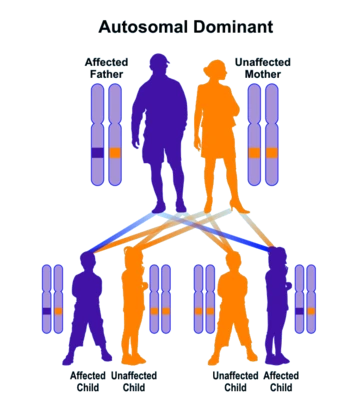
Autosomal dominant inheritance leads to a vertical pattern of transmission
Diagnosis and Prognosis
The clinical features at birth may not suggest the diagnosis of Baker-Gordon Syndrome. The lack of normal development in early childhood should arouse suspicion of a neurodevelopmental disorder. And later the clinical picture could become more specific. Pediatric neurologists, orthopedists and ophthalmologists should be part of the evaluation and management team.
No specific treatment is available for this condition but physical therapy and special education can be helpful. Hypermetropia (farsightedness) corrected with glasses in selected cases may assist children in their educational experience and could decrease the degree of esotropia.
Printer Friendly Version: Ctrl/Cmd+P