


OMIM ID:
Spinocerebellar Ataxia 7
Alternate Names
Defective Genes
Clinical Characteristics
Ocular Features
Pigmentary changes in the retina are somewhat variable but often begin with a granular appearance in the macula and spread into the periphery. The macula often becomes atrophic and dyschromatopsia is common. Retinal thinning is evident, especially in the macula. Decreased visual acuity and loss of color vision are early symptoms and the ERG shows abnormalities of both rod and cone function. External ophthalmoplegia without ptosis is a frequent sign. Most adults and some children eventually are blind.
Systemic Features
Symptoms of developmental delay and failure to thrive may appear in the first year of life followed by loss of motor milestones. Dysarthria and ataxia are nearly universal features while pyramidal and extrapyramidal signs are more variable. This can be a rapidly progressive disease and children who develop symptoms by 14 months are often deceased before two years of age. However, adults with mild disease can survive into the 5th and 6th decades. Peripheral neuropathy with sensory loss and motor deficits are usually present to some degree but the range of clinical disease is wide. Cognitive decline and some degree of dementia occur sometimes.
Genetics
Inheritance
Spinocerebellar ataxia 7 is caused by expanded trinucleotide repeats (CAG) in the ATXN7 gene (3p21.1-p12) and inherited in an autosomal dominant pattern. The number of repeats is variable and correlated with severity of disease. Most patients with 36 or more repeats have significant disease. This disorder is sometimes classified as a progressive cone-rod dystrophy. It is sometimes referred to as olivopontocerebellar atrophy type III or OPCA3.
This disorder exhibits genetic anticipation especially with paternal transmission as succeeding generations often have earlier onset with more severe and more rapidly progressive disease. This is explained by the fact that younger generations tend to have a larger number of repeats and sometimes the diagnosis is made in children before the disease appears in parents or grandparents.
Spinocerebellar ataxia 1 (164400) is a similar autosomal dominant disorder with many of the same clinical and genetic features. It is caused by excess CAG repeats on the ATXN1 gene on chromosome 6.
Pedigree
Autosomal dominant
Autosomal dominant disorders require only one mutation for the disease to be expressed. Since an affected parent has two chromosomes, only one of which has the mutant gene, parents can expect that half (50%) of their children will receive that one and inherit the disease. It is common for individuals that inherit the mutation, however, to not have evidence of the disease (nonpenetrance).
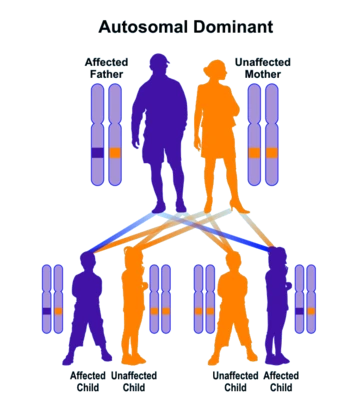
Autosomal dominant inheritance leads to a vertical pattern of transmission