


OMIM ID:
Neurofibromatosis Type I
Alternate Names
Defective Genes
Clinical Characteristics
Ocular Features
Melanocytic iris hamartomas, sometimes called Lisch nodules, are considered pathognomonic of this disease but are found in only about 75% of patients. These appear as sharply defined, smooth masses on the stromal surface and consist of spindle cells of melanocytic origin. Their presence correlates with the severity of skin freckles and cafe-au-lait spots. Also characteristic of neurofibromatosis 1 are eyelid fibromas causing ptosis and the familiar horizontal S-sign in the upper lid margin but these are only found in one-third of patients. Ciliary body cysts have been reported to occur at a frequency of 78%, or 10 times more frequently than in unaffected individuals. Nearly half of patients have occludable anterior chamber angles (Types 1 and 2).
Gliomas of the optic nerves, chiasm or optic tracts are slow growing astrocytomas that occur in about 15% of children at a mean age of about 5 years. While these comprise the most common intracranial tumors in NF1, they typically have a benign course and may even regress. However, some present as precocious puberty and severe loss of acuity may occur before discovery.
Vascular lesions of the retina are also sometimes seen and may be responsible for rubeosis and neovascular glaucoma.
Systemic Features
Vascular anomalies are often seen and those that impact blood supply to the kidneys can induce severe hypertension especially in children (pheochromocytomas are also a risk). Coarctations and aneurysmal anomalies can obstruct the blood supply to major organs, sometimes acutely. Some degree of cognitive impairment and sometimes mental retardation can be seen in nearly half of patients, even in the absence of other obvious neurological deficits. Short stature, tibial pseudoarthrosis, sphenoid dysplasia, and scoliosis are common. Osteopenia and frank osteoporosis are seen in approximately half of patients. A small percentage of patients develop malignant peripheral nerve sheath tumors (lifetime risk 8-13%). Rare patients develop other malignancies, primarily sarcomas.
Diagnosis is based on the presence of some combination of typical features such as cafe-au-lait spots, Lisch nodules, neurofibromas, optic pathway gliomas, axillary or groin freckling, and bone dysplasia. The underlying disease is progressive and the accuracy of diagnosis improves in older patients.
Genetics
Inheritance
The typical disease is caused by mutations in the NF1 gene (17q11.2) and inherited as an autosomal dominant disorder. However, about half of patients have new mutations with males having the higher mutation rate. Penetrance is nearly 100% among those who have mutations in NF1. There is evidence that the gene product is a tumor suppressor protein (neurofibromin) and the clinical features can also result from deactivation of both copies of the gene via the two hit mechanism of Knudson. This has been proposed as a mechanism to explain the high degree of variability of clinical disease within families as the expression depends upon which cell lines experience postzygotic somatic mutations.
Watson syndrome (193520) is also the result of NF1 mutations and shares some clinical features such as neurofibromas, Lisch nodules, shortness of stature, cognitive deficits, and cafe-au-lait spots. It may be an allelic disorder.
Neurofibromatosis type II (101000), with less cognitive problems, results from mutations in NF2. Lisch nodules are less common in type II but acoustic neuromas are more common than in type I.
Pedigree
Autosomal dominant
Autosomal dominant disorders require only one mutation for the disease to be expressed. Since an affected parent has two chromosomes, only one of which has the mutant gene, parents can expect that half (50%) of their children will receive that one and inherit the disease. It is common for individuals that inherit the mutation, however, to not have evidence of the disease (nonpenetrance).
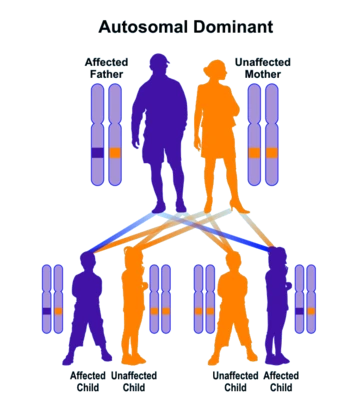
Autosomal dominant inheritance leads to a vertical pattern of transmission