


OMIM ID:
Myotonic Dystrophy 1
Alternate Names
Defective Genes
Clinical Characteristics
Ocular Features
Posterior subcapsular cataracts may be seen at any age, often with striking iridescent opacities in the overlying cortex as well. These polychromatic lens changes can be diagnostic but are present in only 50% of young adults with myotonic dystrophy. When present, they are almost always bilateral. Proximal muscle involvement leads to ptosis, strabismus, weakness of the orbicularis oculi, and sometimes ophthalmoplegia. Such muscle weakness may lead to exposure keratitis.
As many as 25% of patients with DM have a pigmentary retinopathy, usually in a butterfly pattern.
A low IOP and even hypotony is sometimes seen. The mean IOP in a series of 51 patients has been reported as 10.9 compared with 15.4 in controls. Using ultrasound biomicroscopy, ciliary body detachments were found in at least one quadrant of all eyes.
Systemic Features
In the congenital form, hypotonia, generalized weakness, mental retardation and respiratory insufficiency are often present. There is a great deal of clinical heterogeneity among patients. Those with mild disease may have only cataracts and mild myotonia with a normal life expectancy. Those with more severe disease (classical myotonic dystrophy) have these signs plus marked muscle weakness and wasting. Cardiac conduction defects with secondary arryhthmias are a significant cause of mortality. Such patients tend to become disabled in adulthood. Symptoms become evident in the second decade or later. Deep muscle pain is common and can be severe. Distal muscle weakness usually begins before facial muscle weakness is apparent. Myotonia often involves the tongue while proximal muscle weakness can cause dysphagia and dysarthria. Such patients may also suffer respiratory distress. Reproductive fitness is reduced in males who can have gonadal atrophy. Frontal balding is common. Some age-related cognitive decline occurs.
Over 60% of patients have a hearing impairment and more than half of these have auditory brainstem response abnormalities. Vestibular hypesthesia is present in 37.5%.
Genetics
Inheritance
Myotonic dystrophy 1 is an autosomal dominant disorder caused by a trinucleotide (CTG) repeat expansion in a region of the DMPK gene (19q13.2-q13.3). The number of repeats varies widely and is roughly correlated with severity of disease. Infants with congenital myotonia usually have the highest number of repeats and have the most severe cognitive deficits. The number can expand during gametogenesis each generation (resulting in the phenomenon of anticipation) and females generally transmit larger numbers. Most infants with congenital myotonia are offspring of affected mothers. Reduced fetal movement and hydramnios are often noted during such pregnancies.
Affected males have few offspring secondary to gonadal atrophy. Affected heterozygous females, however, do not have the expected ratio of affected offspring because of the dynamic nature of the number of repeats. The risk of an affected offspring for a nulliparous afflicted female is only 3-9% and she has a 20-40% risk of recurrence after the birth of an affected child.
In a study of sibships with myotonic dystrophy, 58% of offspring were affected when the transmitting parent was male and 63% when the transmitting parent was female.
At least some of the variable transmission risks and clinical heterogeneity may be explained by somatic instability of the CTG repeat numbers. The degree of instability, moreover, may also be heritable. Age of onset, for example, is modified by the level of somatic instability. Further, patients in whom the repeat expands more rapidly develop symptoms earlier.
A similar disorder, myotonic dystrophy 2 (602668), is caused by a tetranucleotide repeat expansion in the CNBP gene.
Pedigree
Autosomal dominant
Autosomal dominant disorders require only one mutation for the disease to be expressed. Since an affected parent has two chromosomes, only one of which has the mutant gene, parents can expect that half (50%) of their children will receive that one and inherit the disease. It is common for individuals that inherit the mutation, however, to not have evidence of the disease (nonpenetrance).
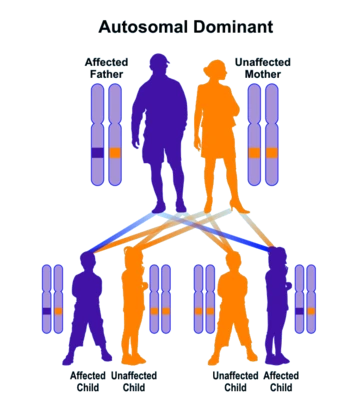
Autosomal dominant inheritance leads to a vertical pattern of transmission