


OMIM ID:
Multiple Endocrine Neoplasia, Type IIB
Alternate Names
Defective Genes
Clinical Characteristics
Ocular Features
Corneal nerves are medullated and appear prominent. Neuromas of the lid margins and sometimes the conjunctiva are common features. Thickening of the entire eyelids may be present.
Systemic Features
Some manifestations may be seen in early childhood. Prominent physical features include full lips, thickened eyelids, high arched palate and a marfanoid habitus. Medullary carcinoma of the thyroid is almost always present and can be the cause of death in relatively young individuals. Metastases are usually to the regional lymph nodes or to liver, lungs, or bone. Pheochromocytomas and megacolon secondary to gastrointestinal neuromas are commonly seen. The esophagus sometimes lacks normal motility for the same reason. Neuromas often lead to thickening of the lips and tongue and can also appear as pedunculated nodules on these structures. Cafe-au-lait spots and increased pigmentation of the hands, feet, and circumoral areas are frequently present. Many patients have dysmorphic features suggestive of Marfan syndrome including a typical habitus, pectus excavatum, scoliosis, and pes cavus. Proximal myopathy and peripheral neuropathy are sometimes seen.
Another form of multiple endocrine neoplasia, called MEN2A, differs in the absence of mucosal neuromas and the marfanoid habitus. MEN2A patients are more likely to have parathyroid hyperplasia.
Genetics
Inheritance
Pedigree
Autosomal dominant
Autosomal dominant disorders require only one mutation for the disease to be expressed. Since an affected parent has two chromosomes, only one of which has the mutant gene, parents can expect that half (50%) of their children will receive that one and inherit the disease. It is common for individuals that inherit the mutation, however, to not have evidence of the disease (nonpenetrance).
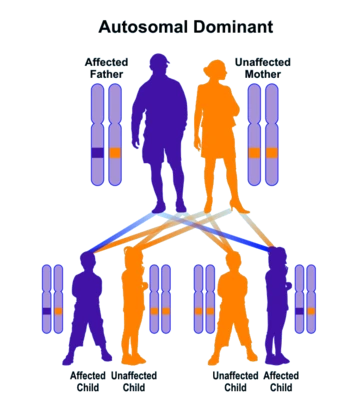
Autosomal dominant inheritance leads to a vertical pattern of transmission