


OMIM ID:
Macular Dystrophy, North Carolina
Alternate Names
Defective Genes
Clinical Characteristics
Ocular Features
North Carolina macular dystrophy is characterized by central macular defects that are present at birth but rarely progress. The fundus findings are highly variable and are usually more dramatic than expected from the visual acuity, which ranges from 20/40 to 20/200, with an average around 20/50. The clinical findings have been classified into different grades: In Grade I, fine drusen-like lesions at the level of the retinal pigmented epithelium are found in the central macular area. Grade II exhibits central confluent drusen with or without pigmentary changes, retinal pigment epithelium atrophy, disciform scar formation or neovascularization. Grade III is characterized by a well-delineated chorioretinal degeneration with hyperpigmentation at the border of the lesion. A central crater-like lesion that affects all retinal layers, as well as the deep choroidal tissue, is a typical finding. It is surrounded by an elevated ridge, which is 3-4 disc diameters size. Color vision and electrophysiological testing are usually normal.
Some patients have choroidal neovascularization that may be responsive to anti-vascular endothelial growth factor treatment.
Although first described in a 4 generation North Carolina family, it has since been found in a variety of ethnic groups and geographic locations.
Systemic Features
No general systemic manifestations are associated with North Carolina macular dystrophy.
Genetics
Inheritance
North Carolina macular dystrophy is an autosomal dominant disorder with high penetration. One locus for the disorder, designated MCDR1 and containing a DNase 1 hypersensitivity site, has been mapped to 6q14-q16.2 and adversely impacts the retinal transcription factor gene PRDM13. Multiple variants in this area have been identified. However, other forms including MCDR2 (608051) resulting from mutations in PROM1 (4p15) and MCDR3 (608850) (linked to a locus at 5p13-p15) have been reported.
The disorder was initially described in a family of Irish descent in North Carolina, and affected individuals have been identified in European, Asian and South American families as well.
Pedigree
Autosomal dominant
Autosomal dominant disorders require only one mutation for the disease to be expressed. Since an affected parent has two chromosomes, only one of which has the mutant gene, parents can expect that half (50%) of their children will receive that one and inherit the disease. It is common for individuals that inherit the mutation, however, to not have evidence of the disease (nonpenetrance).
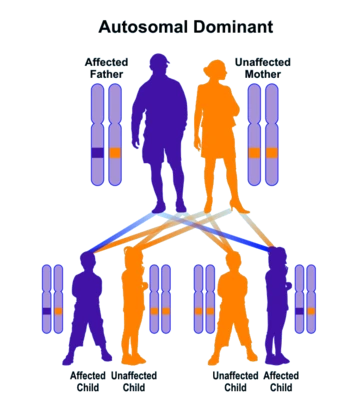
Autosomal dominant inheritance leads to a vertical pattern of transmission