


OMIM ID:
Kabuki Syndrome 1
Alternate Names
Defective Genes
Clinical Characteristics
Ocular Features
The facial features and specifically the periocular anomalies are diagnostic and responsible for the eponymic designation (resembling the make-up of actors of a Japanese theatrical form known as Kabuki). The lid fissures are long and narrow and the lateral third of the lower lids are often everted. The eyebrows are highly-arched and broad with some sparsity especially in the lateral portion. The eyelashes are thick and ptosis is often noted. Strabismus may be present. Blue sclerae have been reported.
Some patients may have extreme microphthalmia.
Systemic Features
Post-natal growth delay and short stature are present as a result of anomalies in the vertebrae often with secondary scoliosis. Persistence of the fetal fingertip pads is common. Hypotonia and joint hypermobility have been noted and some degree of intellectual disability is common. Seizures have been reported but these are not common. Cleft lip and palate are seen in about a third of patients and the palate is highly arched in about 75%. The teeth are small, frequently malformed and widely spaced. Feeding difficulties are common. Anal anomalies such as imperforate anus, anovestibular fistulas, and an anteriorly placed opening may be present, especially in females. A small penis, hypospadias, and cryptorchidism are common in males.
An ill-defined immune deficit seems to be a common feature as evident by susceptibility to infections, primarily otitis media in infants and later recurrent sinopulmonary infections. The majority of patients have hypogammaglobulinemia with a variable pattern of antibody abnormalities resembling common variable immune deficiency and especially low levels of serum IgA.
Hearing loss is seen in nearly half of patients, some of which is no doubt due to recurrent otitis media but CT radiography has demonstrated dysplastic morphology of inner ear structures and the petrous bone. The ears are large and cupped and preauricular pits may be present as well.
Biliary atresia and a variety of morphological anomalies of the kidney have been reported. Renal failure can occur. Perhaps as many as 58% of patients have congenital heart defects, mostly septal in location.
Genetics
Inheritance
Heterozygous mutations in KMT2D (12q13.12) (also called MLL2) are responsible for Kabuki syndrome 1 but parental transmission to offspring is rare and the majority of patients occur sporadically. There is also an X-linked form (Kabuki 2) caused by mutations in KDM5A (Xp11.3). Insufficient clinical data regarding the X-linked phenotype so far has precluded the ability to distinguish the two disorders without genotyping.
Residual genetic heterogeneity remains, however, as a substantial proportion of patients do not have mutations in the two mutant genes known.
Pedigree
Autosomal dominant
Autosomal dominant disorders require only one mutation for the disease to be expressed. Since an affected parent has two chromosomes, only one of which has the mutant gene, parents can expect that half (50%) of their children will receive that one and inherit the disease. It is common for individuals that inherit the mutation, however, to not have evidence of the disease (nonpenetrance).
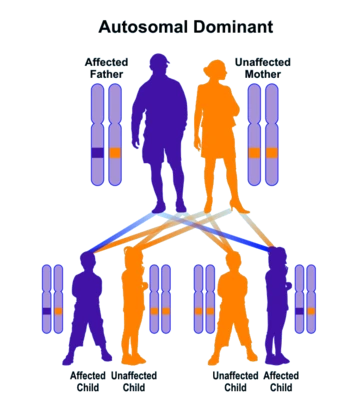
Autosomal dominant inheritance leads to a vertical pattern of transmission
Treatment & Management
There is no general treatment for this condition. Management guidelines are available (Management of Kabuki Syndrome).