


OMIM ID:
Duane Retraction Syndrome 2
Alternate Names
Defective Genes
Clinical Characteristics
Ocular Features
Duane retraction syndrome is a clinically and genetically heterogeneous condition with a highly variable phenotype. It is a congenital and non-progressive strabismus syndrome. Most cases occur sporadically but others are familial and about 30% of affected individuals have other congenital anomalies. It is also seen as part of other syndromes such as Goldenhar (164210), and Wildervanck (314600). In the absence of other anomalies, it is called isolated Duane syndrome. Three heritable types with autosomal dominant familial patterns have also been defined. Patients with type 2 discussed here are more likely to have an exotropia with a head turn toward the uninvolved side when only one eye is involved compared with Duane syndrome type 1 (126800) in which an esotropia with a head turn to the involved side is more common. However, the clinical features are highly variable although intrafamilial differences may be less than those between families.
Sporadic cases are mostly unilateral while familial ones are more likely to be bilateral. The essential features are globe retraction upon adduction with narrowing of the lid fissure and some limitation of abduction. Vertical deviation during adduction is sometimes seen. Frank strabismus in primary position is evident in as many as 76% of individuals and a compensatory head turn is often adopted. Still, amblyopia occurs in at least 10% of individuals. Females are affected more frequently than males.
At one point the syndrome was considered to be a myopathic disorder based on histologic changes in the lateral rectus but current thought based on MRI and neurohistologic studies favors a neuropathic etiology. The abducens motor neurons and the sixth nerve may be absent or dysplastic. Branches of the third nerve may also co-innervate the lateral and medial rectus muscles. EMG studies have documented simultaneous activation of the two muscles which likely accounts for at least some of the globe retraction. However, hypoplastic muscles, including the superior oblique, superior rectus, and levator, have also been visualized on MRI.
Systemic Features
A variety of skeletal and uroglogic anomalies have been found in association with the ocular findings of Duane syndrome but no consistent pattern has been documented.
Genetics
Inheritance
Familial isolated Duane syndrome 2 individuals usually appear in an autosomal dominant pattern of inheritance caused by a mutation in CHN1 (2q31-q32.1). The protein products appear to be involved in early neurological development and are critical to the formation of the cranial nerves that innervate the extraocular muscles.
Mutations in CHN1 are usually absent in nonfamilial cases of Duane syndrome.
For other forms of autosomal dominant Duane syndrome, see Duane Retraction Syndrome 1 (126800) and Duane Retraction Syndrome 3 (617041).
Pedigrees consistent with presumed autosomal recessive inheritance have also been reported but the responsible genes are unknown.
Features of Duane syndrome are also part of the Duane-Radial Ray Syndrome (607323).
Pedigree
Autosomal dominant
Autosomal dominant disorders require only one mutation for the disease to be expressed. Since an affected parent has two chromosomes, only one of which has the mutant gene, parents can expect that half (50%) of their children will receive that one and inherit the disease. It is common for individuals that inherit the mutation, however, to not have evidence of the disease (nonpenetrance).
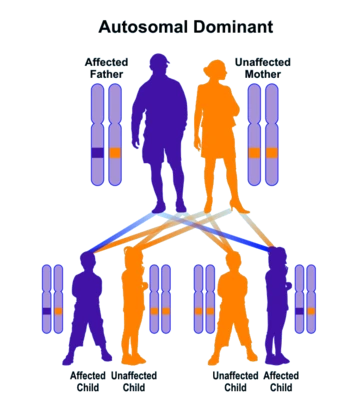
Autosomal dominant inheritance leads to a vertical pattern of transmission